

❋
Erectile Dysfunction
What is erectile dysfunction
Erectile dysfunction means difficulty getting or keeping an erection firm enough for sex, consistently enough that it's a problem for you. Occasional trouble is normal and universal. A persistent pattern is a medical condition, and it is treatable at every level of severity.
It is also extremely common. Most men who have it never bring it up, which is the main reason it goes untreated for years.
Why it happens
An erection is a vascular event that depends on healthy blood vessels, intact nerves, adequate hormone levels, and the tissue of the penis itself being able to hold blood. Anything that interferes with one of those can cause ED.
The common causes:
Vascular disease — the same process that narrows arteries in the heart narrows the much smaller arteries in the penis, usually earlier
Diabetes, which affects both blood vessels and nerves
Prostate cancer treatment — surgery or radiation can injure the nerves that trigger an erection
Peyronie's disease, where scar tissue in the penis causes curvature, pain, and sometimes loss of rigidity
Medications, particularly some blood pressure drugs and antidepressants
Low testosterone, less often than people assume
Smoking, obesity, and inactivity
One thing worth taking seriously
ED can be the first sign of cardiovascular disease, often appearing years before chest pain does. If you have new ED and haven't had a recent cardiac check, that's worth doing regardless of what you decide about treatment.
Treatments before surgery
Most men start here, and most men do well here. Surgery is for men these options have failed or who can't tolerate them.
Oral medications (sildenafil, tadalafil, and others). Effective for many men. They require intact nerves to work, which is why they often disappoint after prostate surgery.
Vacuum erection device. A pump and constriction ring. Mechanical, no drugs, works when medications don't. Some men find it awkward; others use it for years without complaint.
Injection therapy. A very fine needle into the side of the penis before sex. This sounds far worse than it is — the needle is smaller than an insulin needle, and it works when nothing oral does, including after nerve injury. We teach the first dose in the office.
Intraurethral suppository. A small pellet placed in the tip of the urethra. Less reliable than injections but needle-free.
Testosterone, only if your level is genuinely low and confirmed on more than one test. Testosterone alone rarely fixes ED.
When to consider surgery
A penile implant becomes the right conversation when:
Pills don't work, or side effects make them intolerable
Injections work but you don't want to keep using them long-term
Nothing has reliably worked since prostate surgery
You have significant Peyronie's curvature along with poor rigidity
You want something that works every time, without planning around a dose
There is no requirement to exhaust every option first. Some men try injections for a year, decide it isn't the life they want, and choose an implant. That's a legitimate reason.
Penile implants
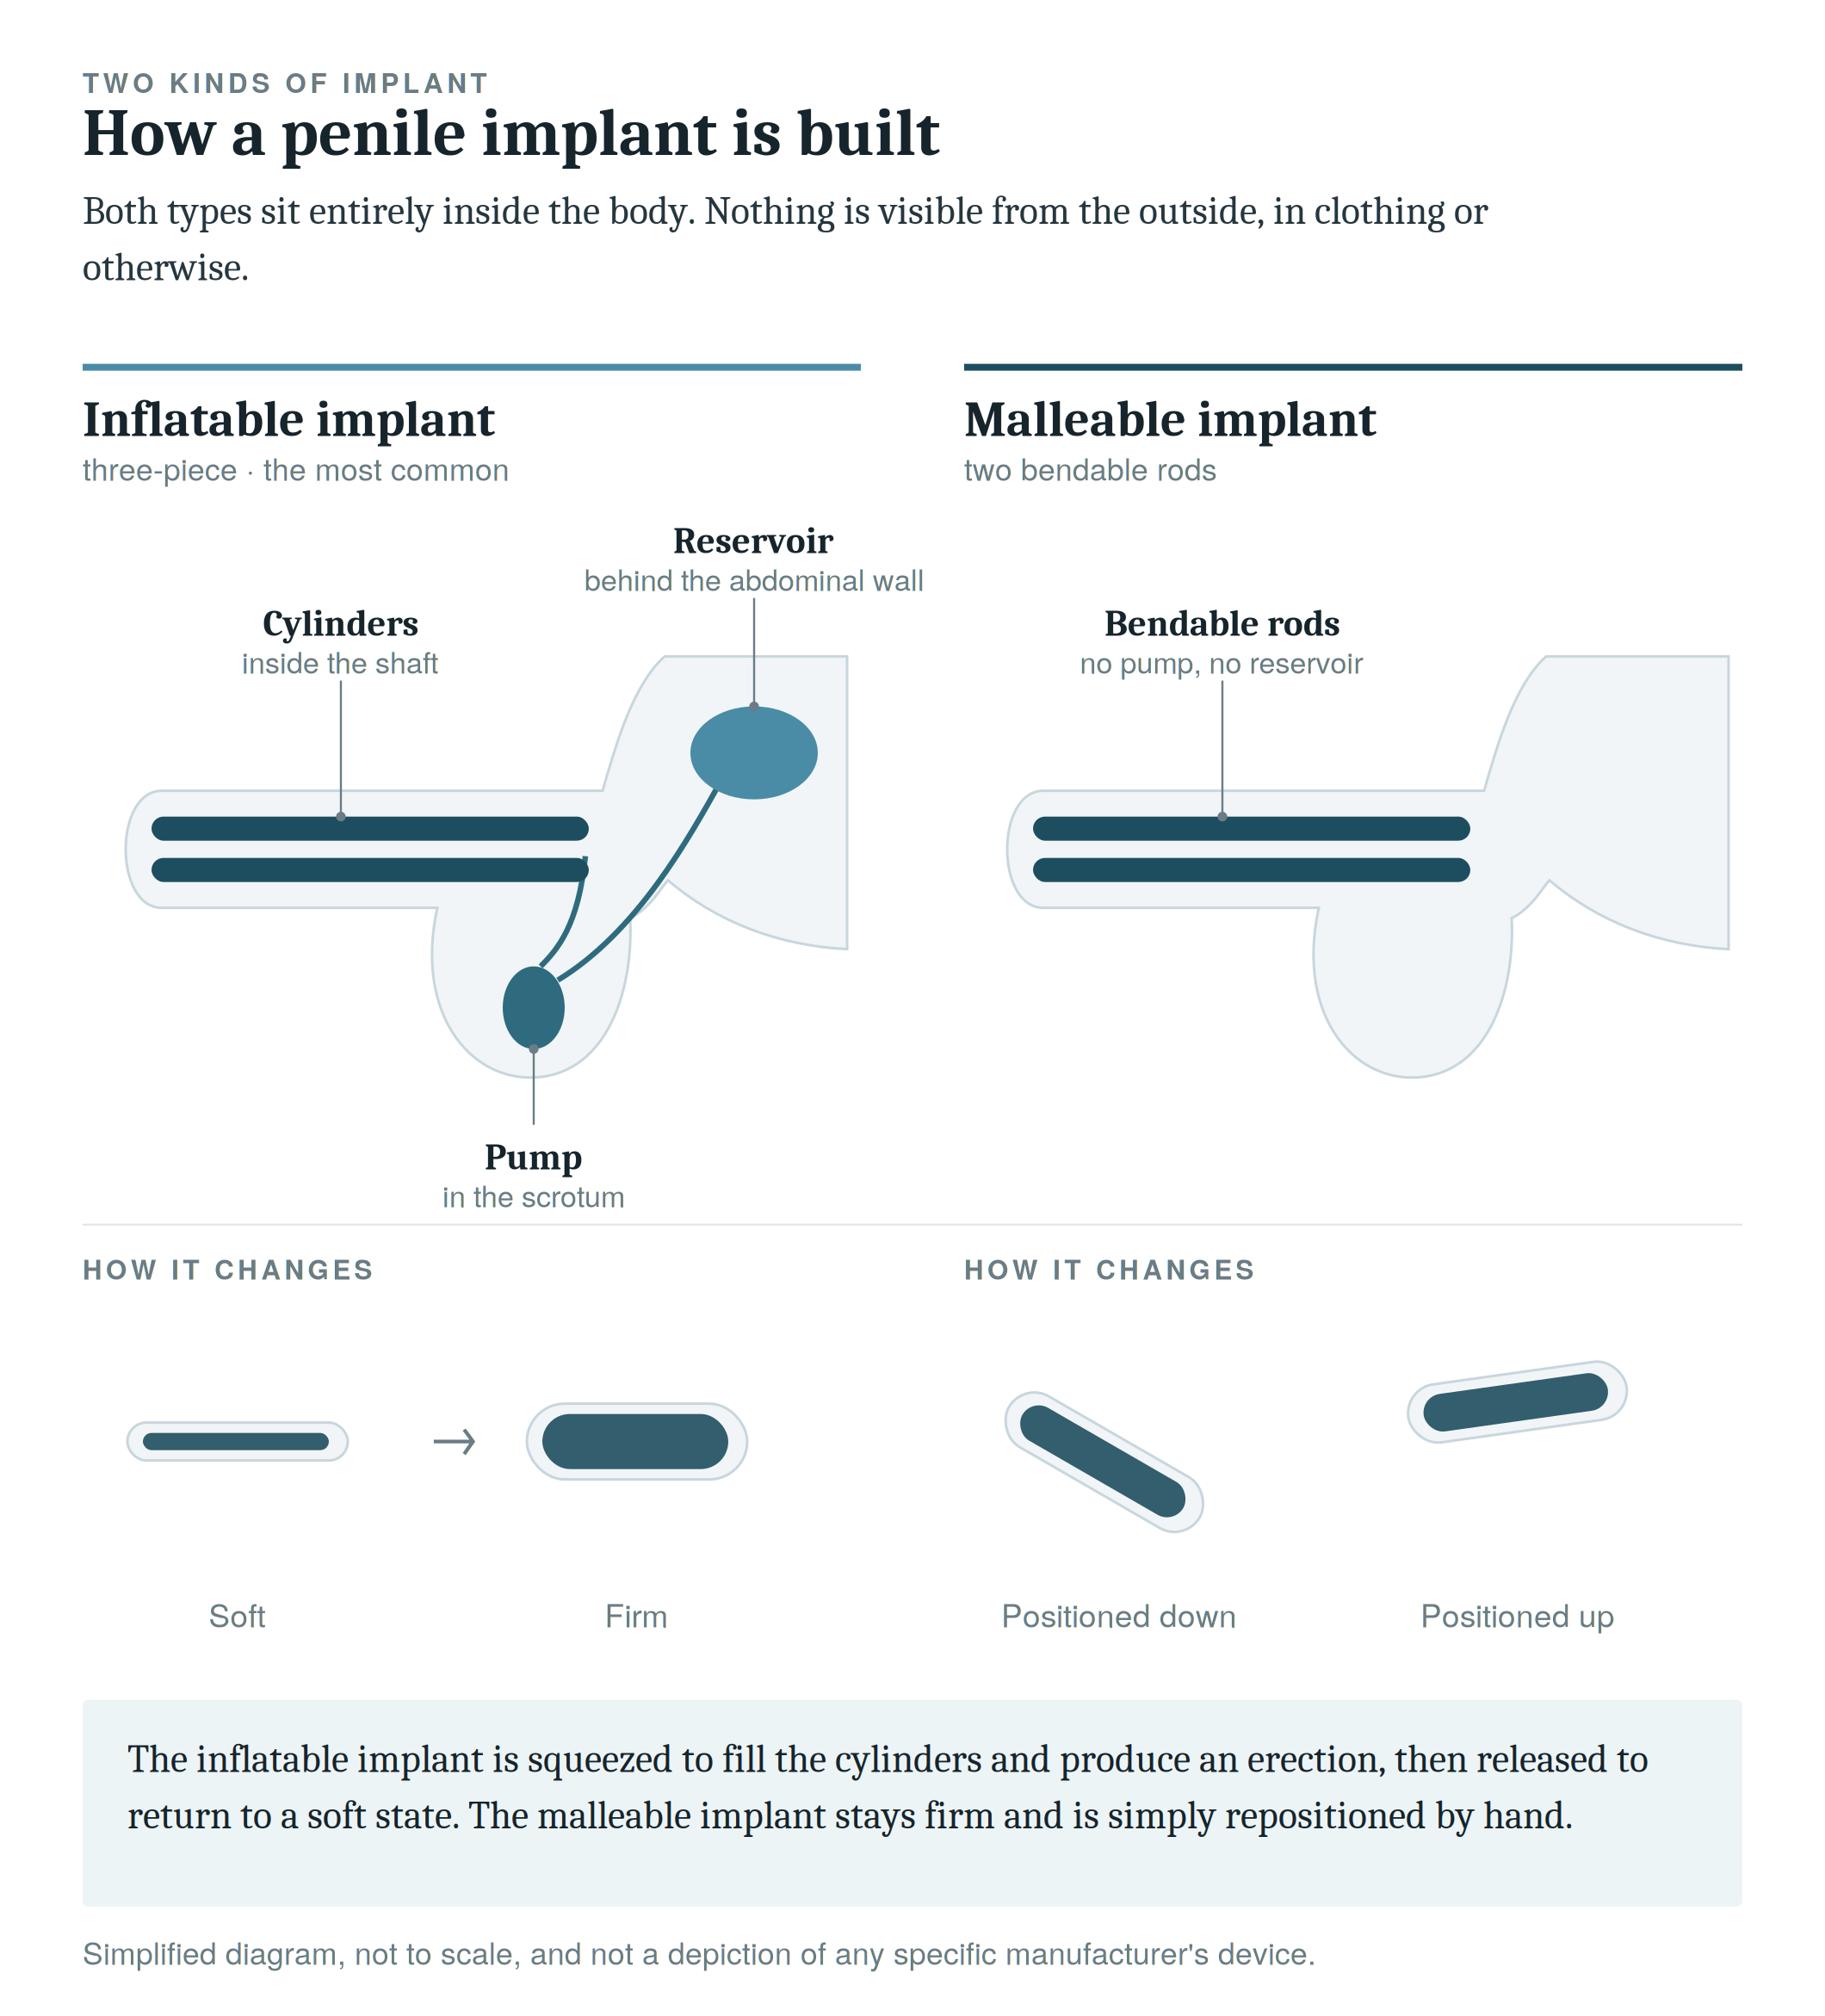
A penile implant, or penile prosthesis, is placed entirely inside the body. Nothing is visible. It replaces the erectile tissue's function rather than trying to stimulate it, which is why it works regardless of nerve damage, blood flow, or diabetes.
Inflatable implant (three-piece)
The most commonly placed device and the one that most closely reproduces a natural erection.
Three connected parts:
Two cylinders placed inside the erection chambers of the penis
A pump placed in the scrotum
A fluid reservoir placed behind the abdominal wall
You squeeze the pump in your scrotum to move fluid into the cylinders, producing an erection you control the timing and duration of. When you're finished, you press a release valve and the penis returns to a soft, natural-looking state.
This is the best option for most men: the flaccid state looks and feels normal, and the erect state is rigid and reliable.
Malleable (semi-rigid) implant
Two bendable rods placed in the erection chambers. The penis stays firm; you position it down for daily life and up for sex.
Simpler, with fewer parts to fail and nothing to operate. It's the better choice for men with limited hand strength or dexterity, men who need to catheterize themselves, or men who want the least complex device. The trade-off is that it doesn't have a truly flaccid state.
What an implant does and doesn't change
It does: produce a reliable erection, every time, without planning.
It doesn't change sensation, orgasm, or desire — the nerves for sensation are separate from those for erection. If you could reach orgasm before, you still can. It doesn't affect fertility or hormone levels.
Be aware: an implant restores rigidity, not length. If ED has been present a long time, or after prostate surgery, some shortening may already have occurred, and the implant works with the length you currently have. This is the single most common source of disappointment, and it's why we discuss it before surgery rather than after.
The natural erectile tissue is used by the implant, so once it is placed, a return to natural erections is not possible. That is a genuine one-way door, and it's why implants come after other options rather than before.
Results
Penile implants have the highest satisfaction rates of any treatment for erectile dysfunction — higher than pills, higher than injections — for both patients and partners. Men who choose them generally wish they had done it sooner.
Most devices continue working for many years, and modern implants are considerably more durable than earlier generations. Some will eventually need replacement.
Risks
Infection. Uncommon, but the most serious complication, because an infected device usually has to be removed. Risk is higher in men with diabetes, particularly if blood sugar is poorly controlled, and in men having a second device placed. Getting your A1c into a good range before surgery genuinely matters.
Mechanical failure of a component, usually years out.
Erosion of a part through tissue, uncommon.
Glans droop, where the head of the penis is less firm than the shaft.
Persistent pain in the early months, which usually settles.
Recovery
Usually same-day surgery. Expect swelling and soreness for a few weeks. The device is left deflated at first and is activated at a follow-up visit, generally around four to six weeks after surgery, once healing allows. Sexual activity resumes after that visit, not before.
Combining procedures
If you have both erectile dysfunction and urinary leakage after prostate surgery, a penile implant and an artificial urinary sphincter can be placed at the same operation or in sequence. Similarly, Peyronie's curvature can be corrected at the time of implant placement. Planning both problems together is usually better than treating them a year apart.

Treatments we'd want you to ask hard questions about
Shockwave therapy, platelet-rich plasma injections, and stem cell treatments are marketed aggressively for ED, often at storefront clinics, often for thousands of dollars paid out of pocket, and often bundled into long contracts signed at the first visit.
These are considered investigational. They are not endorsed by urologic guidelines for routine use, and evidence for durable benefit is not established. That doesn't mean they will never have a role — it means the evidence isn't there yet, and you should not be paying for them under the impression that it is.
If a clinic guarantees results, sells packages up front, or won't tell you what medication they're injecting, leave.
Common questions
Will anyone be able to tell I have an implant? Not in clothing, and not in a locker room. A partner will know it's there.
Does it feel natural? The erection is firm and reliable. Most men and partners describe it as very close to natural; some notice a difference. Sensation and orgasm are unchanged.
How long does it last? Many years for most men. Some devices eventually require replacement, which is a simpler operation than the first one.
I'm diabetic. Can I still have one? Yes, and diabetic men are among those who benefit most, since medications often fail them. We'll want your blood sugar well controlled first to lower infection risk.
Can I have an MRI afterward? Discuss this with us and confirm before scheduling — the answer depends on your specific device.
What if I change my mind later? Implants can be removed, but natural erections do not return. Be sure before you proceed.
Questions worth asking at your consultation
Which type of implant would you recommend for me, and why?
Given my diabetes / prior surgery / radiation, what is my specific infection risk?
What length should I realistically expect?
How many of these do you place a year?
If I have leakage too, should we address both at once?
What does my insurance cover?
To schedule a consultation and discuss which option is right for you, please visit our CONTACT page.